How Can Labs Spot Hemolysis Before LC-MS/MS?
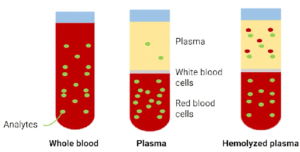
Labs can spot hemolysis before LC-MS/MS by combining fast visual checks with objective screening tools and a controlled pre-analytical workflow. Hemolysis releases intracellular components such as hemoglobin, potassium, enzymes, and phospholipids into plasma or serum, changing the sample matrix before analysis begins. Those changes can distort analyte recovery, increase ion suppression or enhancement, and weaken method reliability. A structured screening process helps teams identify compromised specimens early, decide whether to reject or flag them, and reduce avoidable repeat work. For bioanalytical testing, that matters because poor sample quality can affect calibration behavior, accuracy, precision, and result interpretation. The most effective approach starts at sample receipt, continues through hemolysis assessment, and ends with documented decisions that protect LC-MS/MS data integrity.
1. Recognize the Early Signs of Hemolysis in Blood Samples
Visual Indicators: Plasma and Serum Color Changes
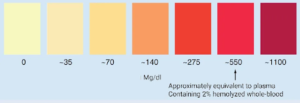
hemolysis labs use visual inspection as the fastest first screen for hemolysis in blood samples. After centrifugation, normal serum or plasma should appear clear and straw-colored. As red blood cells rupture, free hemoglobin discolors the supernatant, shifting it from faint pink to red depending on severity. A light pink tint may indicate mild hemolysis, while deeper red suggests a larger release of intracellular material. Labs should inspect samples under consistent lighting and against a white background so subtle color changes are easier to detect. This simple check helps separate clearly acceptable specimens from obviously compromised ones before LC-MS/MS preparation starts. Visual grading also gives staff a practical way to prioritize confirmatory testing when sample volume is limited.
Hidden Signs That Visual Inspection Can Miss
Visual review alone cannot catch every hemolyzed sample. Mild hemolysis may not produce an obvious color shift, especially in small-volume tubes, dark collection containers, or samples with naturally deeper pigmentation. Lipemia and icterus can also mask the pink to red discoloration associated with free hemoglobin, making visual interpretation less reliable. In some cases, a sample may appear acceptable after centrifugation even though enough intracellular content has leaked to alter matrix composition and interfere with LC-MS/MS performance. That hidden burden can affect extraction efficiency, internal standard response, and analyte signal stability. For that reason, labs should treat visual inspection as an initial screen, not a final decision tool, and confirm questionable samples with objective hemolysis testing.
2. Apply Reliable Methods to Detect Hemolysis Before LC-MS/MS
Use Hemolysis Index and Spectrophotometric Testing
The most reliable way to detect hemolysis before LC-MS/MS is to measure it objectively. A hemolysis index uses absorbance data to estimate free hemoglobin in serum or plasma, giving labs a standardized result rather than a subjective visual impression. Spectrophotometric testing strengthens screening because hemoglobin has characteristic absorbance patterns that can be measured quickly and reproducibly. This approach supports high-throughput sample triage, especially when visual appearance is unclear or potentially masked by lipemia or icterus. Labs should define acceptance thresholds in their SOPs and link those thresholds to downstream actions such as accept, flag, investigate, or reject. When methods are validated against matrix quality criteria, hemolysis index testing becomes a practical control that protects sample suitability before extraction and LC-MS/MS analysis.
Assess Hemolysis-Related Matrix Effects Before LC-MS/MS
Detecting hemolysis is only part of the job; labs also need to understand how it affects method performance. Hemolysis can introduce phospholipids, proteins, and cellular debris that alter extraction recovery and drive ion suppression or enhancement during LC-MS/MS. A useful workflow compares hemolyzed and non-hemolyzed matrices during validation or fit-for-purpose studies to quantify bias, internal standard behavior, and precision shifts. Post-column infusion, matrix factor assessment, and recovery experiments help identify where interference occurs. These checks allow teams to set evidence-based rejection limits instead of relying on appearance alone. If a method shows measurable vulnerability to hemolyzed specimens, that risk should be documented clearly in sample handling guidance so analysts can make fast, defensible decisions before full analytical work begins.
3. Build a Pre-Analytical Workflow to Manage Hemolyzed Samples
Identify, Document, and Evaluate Sample Quality
A strong pre-analytical workflow starts the moment samples arrive. Staff should inspect tube condition, verify labeling, review transport history, and check for visible hemolysis after centrifugation. Any concern should be documented immediately, including appearance, hemolysis index result, collection notes, and chain-of-custody details. Consistent documentation helps labs trace recurring issues back to collection, handling, or shipping steps and supports defensible decisions when samples must be flagged or rejected. Evaluation should follow predefined SOP criteria rather than individual judgment alone. That means assigning clear disposition categories, recording who made the assessment, and noting whether confirmatory testing was performed. With this structure in place, labs can identify compromised specimens early and prevent questionable samples from moving into extraction and instrument time unnecessarily.
Prevent Hemolysis and Protect LC-MS/MS Data Integrity
Preventing hemolysis is more efficient than managing it after receipt. Labs and collection teams should use proper venipuncture technique, avoid excessive suction, choose suitable needle sizes, and minimize forceful transfer between containers. Samples should be mixed gently, processed within defined timelines, and centrifuged under validated conditions to reduce cell rupture. Temperature control during storage and shipment also matters because extreme heat, freezing before separation, or repeated freeze-thaw exposure can damage red blood cells. Training and SOP reinforcement are essential, especially when multiple collection sites feed one bioanalytical workflow. By reducing pre-analytical stress on specimens, labs preserve matrix consistency, limit avoidable matrix effects, and improve confidence that LC-MS/MS results reflect the analyte concentration rather than damage introduced before analysis began.
Conclusion
Labs can spot hemolysis before LC-MS/MS by using a layered process: inspect sample appearance, confirm with hemolysis index or spectrophotometric testing, and apply SOP-based decisions within a controlled pre-analytical workflow. That combination is effective because hemolysis is both a visible quality issue and a matrix problem that can directly affect extraction, ionization, and result quality. Visual checks provide speed, objective testing provides consistency, and method-specific matrix effect studies provide the evidence needed for acceptance limits. When documentation and prevention measures are built into routine sample handling, labs can catch compromised specimens earlier and reduce unnecessary reruns or questionable data. The result is stronger bioanalytical reliability, better use of instrument time, and greater confidence in every LC-MS/MS result released.





