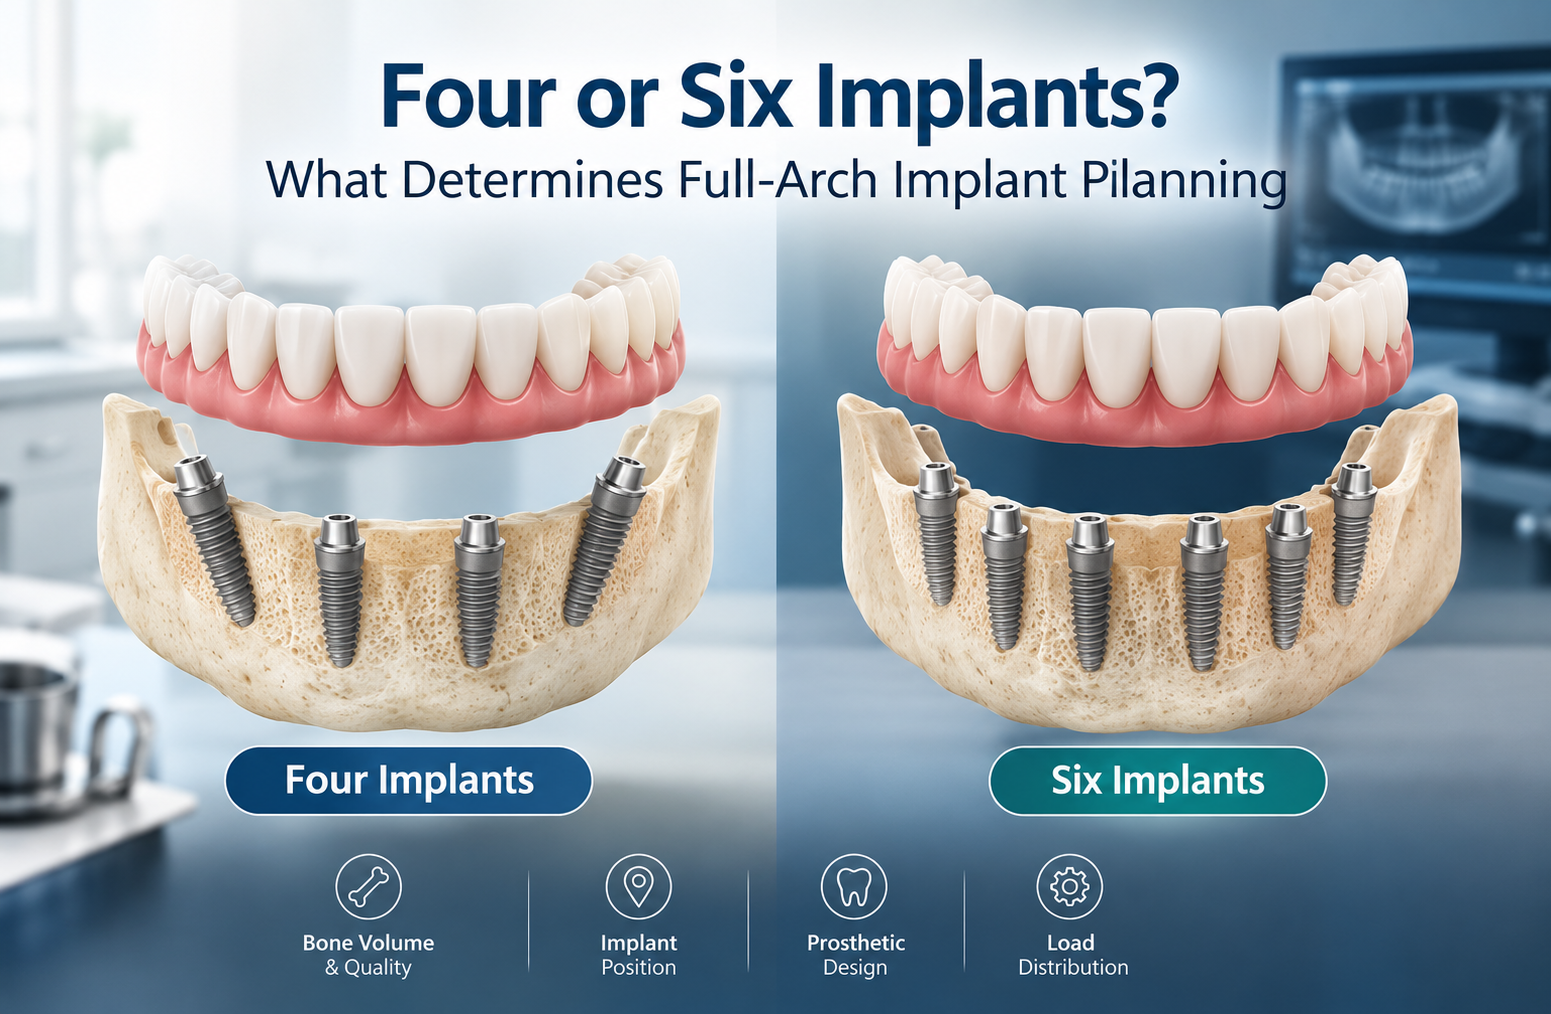
Four or Six Implants? What Determines Full-Arch Implant Planning
A patient arrives expecting a straightforward choice. Four implants sound like the standard package; six sound like the upgraded version. If six supports a full arch, the patient may reasonably assume that six must mean a stronger or better result. But that is not how the decision is made.
In full-arch rehabilitation, the number of implants is only one part of the design. The clinical question is whether the available bone, implant positions, prosthetic design, and expected functional loads can provide a stable foundation. Recent systematic reviews have found broadly similar clinical outcomes between four- and six-implant full-arch approaches, reinforcing that neither configuration is automatically superior.
The jaw decides more than the brochure does
The first question is not “How many implants do you want?” It is “Where can implants be predictably placed?”
Bone volume matters because an implant needs sufficient dimensions and a suitable position to achieve primary stability and support the prosthesis. Bone density matters too, particularly when immediate loading is planned: clinical research on full-arch treatment has found bone density to have a significant effect on primary stability, while biomechanical modelling has shown that lower-density cancellous bone can increase implant micromotion under load.
A four-implant concept commonly uses two anterior implants and two posterior implants, with the posterior implants often tilted to improve anteroposterior spread and reduce the need for long cantilevers. The approach has also been used to work around anatomical constraints in atrophic jaws.
A six-implant design gives the clinician two additional points of support, but implants cannot simply be added wherever bone is available. Implant number, dimensions, and three-dimensional distribution have to be considered together. A recent consensus statement notes that when adequate implant geometry cannot be achieved because of ridge atrophy or anatomical limitations, six implants can be preferable to four with undersized terminal implants.
Load distribution is the other half of the decision
A full-arch prosthesis does not load every implant identically. Where implants are positioned, how far apart they are, the length of any cantilever, and the direction of chewing forces all affect how stress reaches the implant-bone system.
Biomechanical studies have repeatedly examined this issue. A review of finite element analyses found that increasing the number of implants reduced stress in some models, although not in all of them. The same review found that reducing cantilever length and using an appropriate distal implant position could improve force distribution. More recent modelling has likewise shown that implant positioning and load distribution can be more important than implant count alone.
That helps explain why “six” is not automatically a higher clinical tier. Six implants may provide additional support when the anatomy and prosthetic plan make that useful, while four strategically positioned implants can provide an appropriate foundation in another patient. The goal is not to maximise the number of fixtures. It is to create a mechanically sensible relationship between the available bone, implant positions and prosthesis.
For readers comparing the two approaches, this overview of the six-implant option explains that configuration, while this discussion of the four-implant approach covers the four-implant concept.
Four or six starts with diagnosis, not preference
The distinction becomes clearer when planning is based on three-dimensional imaging rather than a treatment menu. Full-arch consensus guidance recommends prosthetically driven 3D planning using CBCT integrated with digital scans, because the proposed prosthesis and available anatomy need to be assessed together.
The clinician also needs to evaluate the ridge, important anatomical structures, implant dimensions and positions, and prosthetic design. The upper and lower jaws do not present identical anatomical problems, so a configuration that makes sense in one arch cannot simply be transferred to another.
Bone density is particularly relevant when the plan involves immediate function. Research on immediate loading has linked primary stability to bone characteristics, and a finite element study of mandibular full-arch restorations found cancellous bone density significantly influenced micromotion. That does not mean low-density bone automatically rules out a particular implant count. It means the surgical and loading plan must account for the mechanical environment actually present in that patient.
Other clinical factors can also change the equation. The 2026 Italian consensus statement identifies systemic risk, periodontal risk, prosthetic design and biomechanical risk among the elements that should be incorporated into full-arch planning. It describes four implants as a baseline configuration for selected mandibular cases with adequate anterior bone volume and favourable implant spread, while identifying higher-biomechanical-risk situations in which six may be considered.
The evidence does not support a simple “more is better” rule
A 2024 systematic review and meta-analysis of fixed maxillary complete dentures found no significant differences between four and six implants in implant or prosthesis survival or mechanical and biological complications. A 2026 systematic review covering 55 studies likewise reported broadly similar outcomes, while noting substantial heterogeneity among the studies.
Biomechanical research can show differences in how particular configurations handle simulated forces, but these models are not a substitute for examining an individual patient’s anatomy.
That distinction matters because a treatment plan is not selected from a leaderboard. It is constructed around the patient’s bone, anatomy, functional demands, and prosthetic requirements.
The question worth asking at the consultation
A patient deciding between four and six implants should therefore ask: “What does my anatomy allow, and how will the planned implants distribute the load of my final prosthesis?”
That answer comes from examination and imaging, followed by prosthetically driven planning. If the available bone supports appropriately sized, well-distributed implants and the expected loads can be managed within a four-implant design, adding two more implants is not automatically necessary. If anatomy, implant dimensions, or biomechanical demands make additional support useful, six may form part of the plan.
The number on the treatment estimate is easy to compare. The bone underneath it is not. And that is precisely why four or six should never be treated as a choice between a basic package and an upgraded one.





